Gastritis and gastric pain
Gastric pain and gastritis are not always the same thing
You feel it high in the stomach, just under the ribs. A burning or gnawing ache, a heavy fullness after half a meal, a wave of nausea.
FRCSEd (General Surgery)Five clinics in Singapore
Dr Sulaiman in his endoscopy suite.
What this article covers
Most people call it gastric.
When it keeps coming back, the real question is whether anything is wrong with your stomach at all. This article explains what gastritis is, what causes it, why gastric pain and gastritis are often two different things, and when the pain is worth a proper look.
Key points
Key points on gastritis and gastric pain
- Gastritis means the lining of the stomach is inflamed, and most people who have it do not feel any symptoms.
- Gastric pain often turns out not to be gastritis. Studies cited by the Asian consensus found no structural cause in 43% to 69% of people investigated for indigestion.
- H. pylori infection is the most common cause of gastritis. Other common causes include anti-inflammatory painkillers, alcohol, bile reflux and autoimmune gastritis.
- Treatment follows the cause, so naming the cause matters more than naming the pain.
- Weight loss, persistent vomiting, anaemia or new indigestion in middle age are reasons to investigate rather than wait.
What gastritis means and how it differs from gastropathy.
Gastritis means the lining of your stomach is inflamed.
Inflamed
Gastritis
The lining of your stomach is inflamed.
Damaged
Gastropathy
The lining is damaged but shows little or no inflammation.
A close relative, gastropathy, means the lining is damaged but shows little or no inflammation. The distinction comes from the US National Institute of Diabetes and Digestive and Kidney Diseases (NIDDK) guidance on gastritis and gastropathy.
It explains why two people with the same “gastric” can leave with different answers.
Doctors also describe gastritis by how it started:
Sudden damage
NIDDK calls this acute erosive gastropathy. It follows severe injury, critical illness or sepsis, or contact with irritants such as alcohol or anti-inflammatory painkillers.
Long-standing inflammation
This is chronic gastritis. The commonest form is H. pylori gastritis, and NIDDK notes that nearly everyone infected with H. pylori develops it.
Gastritis is a finding, not a feeling.
It is confirmed by looking at the lining. NIDDK describes the diagnosis as a history, an examination and, where needed, an upper gastrointestinal endoscopy with small tissue samples.
Why gastric pain and gastritis are not always the same thing.
Two facts pull in opposite directions here, and both matter.
First, gastritis is often silent. NIDDK states that the majority of people with gastritis or gastropathy have no symptoms.
So a stomach that feels fine can still be inflamed.
Second, gastric pain often has no gastritis behind it. Doctors call persistent upper stomach pain dyspepsia.
The 2017 American College of Gastroenterology and Canadian Association of Gastroenterology guideline (Moayyedi P, et al. Am J Gastroenterol 2017) defines it as pain in the upper abdomen, lasting at least 1 month, as the main complaint.
When a gastroscopy finds nothing to explain it, the label becomes functional dyspepsia.
How often does that happen? The Asian consensus report on functional dyspepsia (Miwa H, et al. J Neurogastroenterol Motil 2012) states that most Asian patients with uninvestigated indigestion and no alarm features have functional dyspepsia.
In one Chinese study it cited, of 782 people with uninvestigated indigestion, 69% had functional dyspepsia. A nine-country Asian study it also cites, which included Singapore, found 43%.
People with uninvestigated indigestion whose gastroscopy found no cause
- Chinese study, 782 people
- 69%
- Nine-country Asian study, including Singapore
- 43%
Gastritis is confirmed by looking at the stomach lining; symptoms alone cannot tell the causes apart.
H. pylori gastritis, painkiller damage and functional dyspepsia are treated differently, which is why the cause matters.
The gastritis symptoms people notice, when there are any.
When gastritis does cause symptoms, NIDDK lists the following:
- Pain or discomfort in the upper abdomen, the classic gastric pain
- Nausea or vomiting
- Feeling full early in a meal
- Loss of appetite
Long-standing gastritis can also show up in less obvious ways.
NIDDK notes that H. pylori gastritis and autoimmune gastritis can interfere with absorbing iron from food, which can cause iron-deficiency anaemia. That can feel like tiredness or breathlessness rather than stomach pain.
These symptoms centre on the upper abdomen. If your pain sits lower down, the list of possible causes is different, and our article on lower abdominal pain covers it.
What causes gastritis, from H. pylori to everyday painkillers.
Most cases come from a short list of causes. The table draws on NIDDK’s causes and treatment pages.
| Cause | What happens to the lining | What usually addresses it |
|---|---|---|
| H. pylori infection | A bacterium lives in the stomach lining and keeps it inflamed for as long as the infection stays | Two or more antibiotics with an acid-reducing medicine |
| Anti-inflammatory painkillers (NSAIDs) | Long-term contact damages the lining | Stopping, lowering the dose or changing the painkiller, or adding an acid-reducing medicine, decided with your doctor |
| Alcohol | Long-term or heavy contact irritates and damages the lining | Cutting down |
| Bile reflux | Bile flows backwards from the small intestine into the stomach | Medicine containing bile acids, or surgery |
| Autoimmune gastritis | The immune system attacks cells in the stomach lining | Iron, folic acid and vitamin B12, sometimes as injections |
| Severe illness or injury | Critical illness, major injury or sepsis causes sudden damage | Treated in hospital alongside the illness |
Less common causes on the NIDDK list include coeliac disease, Crohn’s disease, chemotherapy, radiation, food allergies, other infections and portal hypertension.
H. pylori deserves a separate word.
NIDDK describes it spreading through contaminated food and water and through saliva, vomit or stool. The Kyoto global consensus on H. pylori gastritis (Sugano K, et al. Gut 2015) agreed unanimously that H. pylori gastritis should be treated as an infectious disease, even when it causes no symptoms.
Our article on H. pylori explains how it is tested and treated.
What antral gastritis means and why the location matters.
The antrum is the lower part of the stomach, the region that leads into the outlet to the duodenum. That is how the US National Library of Medicine’s MeSH entry for the pyloric antrum defines it.
“Antral gastritis” on a gastroscopy report describes where the inflammation was seen. It is not a separate disease, and the cause still needs to be found.
Location matters because it changes what the stomach does.
The Kyoto consensus (Statement 3) agreed that it is useful to describe H. pylori gastritis by the part of the stomach involved, because the risks of ulcers and of gastric cancer follow the pattern.
A review by Malfertheiner P (Dig Dis 2011) sets out the two broad patterns:
Lower stomach
Antrum-predominant gastritis
With little involvement of the upper stomach, goes with higher acid output and a tendency to duodenal ulcers.
Main body of the stomach
Corpus-predominant gastritis
In the main body of the stomach, especially with thinning of the lining (atrophy), goes with lower acid output and carries the highest risk of gastric cancer.
If your report says antral gastritis, two questions are worth asking.
Was H. pylori tested for? And were biopsies taken?
How gastritis relates to stomach ulcers and bleeding.
Gastritis and stomach ulcers share their two main causes.
Inflamed lining
Gastritis
A break in the lining
A peptic ulcer
Bleeding
Which may be severe
An ulcer is a sore on the lining of the stomach or duodenum, and NIDDK names H. pylori and NSAID painkillers as its two most common causes.
NIDDK also notes that acute erosive gastropathy can lead to peptic ulcers and to bleeding, which may be severe.
So inflammation of the lining and a break in the lining sit on the same path, which is why they are often found together.
Our separate article on stomach ulcer symptoms and causes covers ulcers in detail. Black stools or vomiting blood point towards bleeding, which is explained on the gastrointestinal bleeding page.
How gastritis is diagnosed and what a gastroscopy adds.
NIDDK describes the usual steps: questions about your symptoms and medicines, an examination, and then tests chosen for your situation.
Questions
Your symptoms and medicines
Examination
Tests
Chosen for your situation
Each test answers a different question.
| Test | What it can tell you | What it cannot tell you |
|---|---|---|
| Urea breath test | Whether H. pylori is present | What the stomach lining looks like |
| Stool test | Whether H. pylori is present | What the stomach lining looks like |
| Blood tests | Anaemia, and clues to other causes or complications | Whether the lining is inflamed |
| Gastroscopy with biopsy | The lining itself: inflammation, erosions, ulcers, and tissue for H. pylori and microscopic changes | Anything about the lower bowel, which needs a separate test |
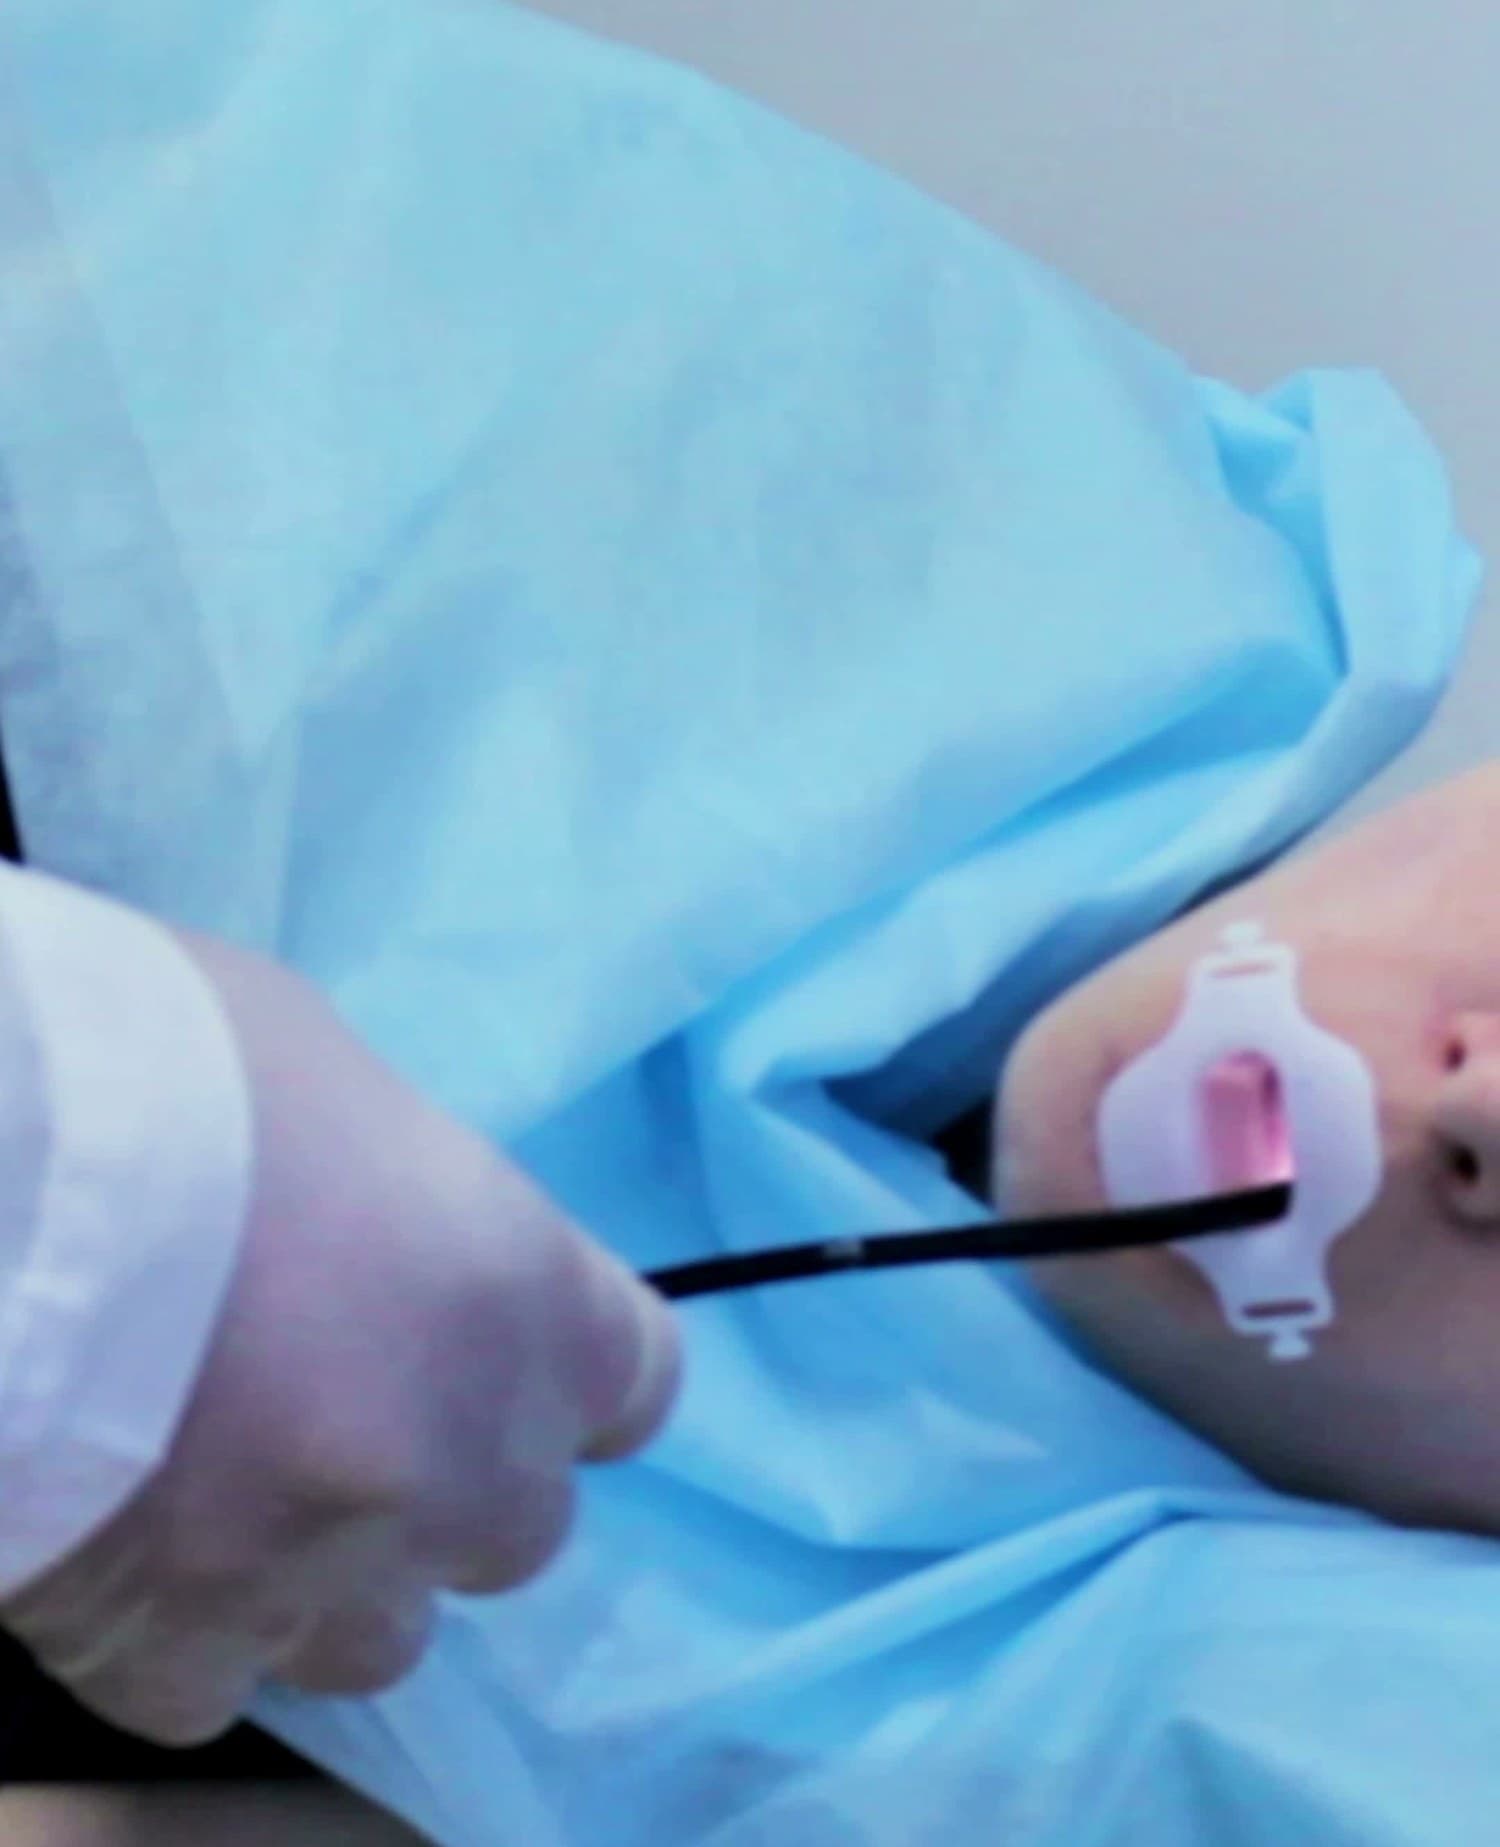
A gastroscopy passes a thin flexible camera through the mouth into the stomach and the first part of the small intestine. Small tissue samples can be taken during the same examination.
It is an invasive procedure, so it carries small risks. NIDDK’s guidance on upper GI endoscopy describes the risks as low and lists a reaction to the sedative, bleeding and, rarely, a perforation (a hole in the lining). These are discussed with you beforehand.
The Kyoto consensus (Statement 4) recommends that the tissue be assessed for inflammation, thinning of the lining (atrophy) and intestinal metaplasia, a change in the lining cells, in different parts of the stomach.
Those changes do not show up on a breath test or a blood test.
When gastric pain is worth a gastroscopy, and when it can wait.
Published guidance does not give one answer here, and the difference is worth knowing.
| Your situation | What the guidance says |
|---|---|
| Upper stomach pain for 1 month or more, under 60, no warning signs | Non-invasive H. pylori test, and treatment if positive (ACG and CAG 2017, Statement 3) |
| Aged 60 or over with indigestion | Gastroscopy (ACG and CAG 2017, Statement 1) |
| Grew up in South East Asia | The age threshold for gastroscopy should be lowered, using clinical judgement (ACG and CAG 2017) |
| New indigestion after 40, 45 or 50, depending on how common upper GI cancer is in your population | Investigate (Asian consensus 2012, Statement 5) |
| Weight loss, worsening difficulty swallowing, persistent vomiting, signs of bleeding, anaemia, fever, or a family history of gastric cancer | Investigate (Asian consensus 2012, Statement 5) |
The North American guideline sets its age threshold at 60. It also notes that upper GI cancer risk is higher in people born and raised in South East Asia.
The Asian consensus sets its thresholds lower. If you are unsure which applies to you, that is a reasonable question to bring to a consultation.
Dr Sulaiman’s own H. pylori article recommends a gastroscopy for people with symptoms, because one examination can answer several questions at once: whether H. pylori is there, how inflamed the lining is, and whether there are erosions, ulcers or precancerous changes. Guidelines differ, as the table shows.
How gastritis treatment depends on what caused it.
There is no single gastritis treatment, because there is no single gastritis.
The NIDDK treatment guidance matches the treatment to the cause.
H. pylori gastritis
Two or more antibiotics, taken with a proton pump inhibitor, which lowers stomach acid. Some regimens add bismuth.
The Kyoto consensus (Statement 17) agreed that people infected with H. pylori should be offered treatment unless there are competing considerations.
It also agreed (Statement 8A) that if indigestion goes away and stays away after successful treatment, the symptoms can be put down to the H. pylori gastritis.
There is a longer-term reason as well. According to the Kyoto consensus (Statement 20), clearing H. pylori is associated with a lower risk of stomach cancer, and the size of that difference depends on how much atrophy is already present when treatment is given.
Painkiller-related damage
Your doctor may suggest stopping the painkiller, lowering the dose, switching to a different one, or adding an acid-reducing medicine.
If the painkiller was prescribed for your heart or another condition, speak to the doctor who prescribed it before changing anything.
Autoimmune gastritis
Iron, folic acid and vitamin B12 to prevent anaemia, with B12 sometimes given as injections.
Bile reflux
A medicine containing bile acids, or surgery.
Lowering acid
Medicines that reduce stomach acid, such as proton pump inhibitors, H2 blockers or sucralfate, are also used.
Treatment is a decision to make with a doctor who knows your history. Results vary from person to person.
What spicy food, alcohol and stress have to do with it.
Much of the everyday advice about gastric pain is about food. The evidence points somewhere else.
NIDDK’s guidance on eating and diet states that eating, diet and nutrition do not play an important role in causing most cases of gastritis or gastropathy.
It names two exceptions. Heavy alcohol use can cause sudden damage to the lining, and food allergies can rarely cause gastritis.
If a particular food reliably sets off your symptoms, avoiding it is sensible.
But avoiding chilli is not treating H. pylori.
Stress works the same way. The stress that appears on the NIDDK list of causes is physical: severe injury, critical illness, sepsis.
Everyday work stress is not on that list.
Questions people ask about gastritis and gastric pain.
Is gastric pain the same as gastritis?
No. Gastric pain is a symptom. Gastritis is inflammation of the stomach lining, confirmed by looking at it. Many people with gastritis feel nothing, and many people with gastric pain have a normal-looking stomach at gastroscopy.
Can gastritis go away on its own?
It depends on the cause. Damage from painkillers or alcohol is treated by removing the irritant, with your doctor's advice. H. pylori gastritis continues for as long as the infection is present, so it is treated by clearing the infection and then confirming it has gone.
Is gastritis serious?
Often it is mild, and many people never know they have it. Long-standing H. pylori gastritis and autoimmune gastritis can lead to thinning of the lining, iron-deficiency anaemia and a higher chance of growths in the stomach lining, which is why the cause is worth finding.
My gastroscopy report says antral gastritis. What does that mean?
It means inflammation was seen in the antrum, the lower part of the stomach. It describes the location, not the cause. Ask whether H. pylori was tested for and whether biopsies were taken, because those results decide the treatment.
What is the difference between gastritis and a stomach ulcer?
Gastritis is inflammation of the lining. An ulcer is a sore on the lining. They share the same two main causes, H. pylori and anti-inflammatory painkillers, and are often found together. Our article on stomach ulcer symptoms and causes explains ulcers in detail.
The bottom line on gastric pain and gastritis.
Gastric pain is a symptom. Gastritis is a finding.
The cause decides the treatment.
If your pain has lasted a month or more, keeps returning after treatment, or comes with any of the warning signs above, it is worth finding out what is actually happening in your stomach rather than guessing.
An H. pylori test answers part of that question. A gastroscopy answers more of it.
If you would like to talk it through, message the clinic on WhatsApp, or see where the clinics are.

The surgeon
The surgeon.
Dr Sulaiman's practice is built around complex colorectal surgery, with robotic-assisted technique as his primary surgical platform for colectomy and anterior resection. He has contributed eight peer-reviewed publications.
Patients consult Dr Sulaiman for his depth of experience in colorectal cancer and perianal conditions, as well as for consultations that are thorough, unhurried, and focused on giving patients a clear understanding of their options.
Former Director of Endoscopy, Changi General Hospital
He led the endoscopy unit at Changi General Hospital, a high-volume diagnostic service covering colonoscopy and gastroscopy across a broad and diverse patient population, and brings that public-sector depth to his private practice.
Book a consultation
Gastric pain that keeps coming back. Find out what is behind it.
If your pain has lasted a month or more, keeps returning after treatment, or comes with any of the warning signs above, it is worth finding out what is actually happening in your stomach rather than guessing. Book a consultation to have it assessed. Appointments are available across five clinic locations in Singapore, and self-referrals are welcome.