Robotic rectal cancer surgery in Singapore
Robotic rectal cancer surgery, deep in the pelvis.
Dr Sulaiman Bin Yusof has performed more than 100 Da Vinci Xi rectal cancer cases.
FRCSEd (General Surgery)Five clinics in Singapore

In short
3D
Vision where it is narrowest
Fewer
Conversions to open surgery
Pooled analyses associate robotic rectal surgery with a lower risk of converting to open surgery, and a conversion itself increases complication risk.
Nerves
Identified and protected
Faster
Recovery than open surgery
His story
Dr Sulaiman Bin Yusof
Senior Consultant Colorectal and General Surgeon, seeing patients at five clinics in Singapore.
- MBChB (Sheffield), M.Med (Surgery), FRCSEd (General Surgery)
- Consults in English and Malay
- MOH Fellowship, Peter MacCallum Cancer Centre, Melbourne
- Singapore Health Quality Service Star Award 2023
- Dean's Honour Roll for Teaching
Five clinics across Singapore
ORCHARD / NAPIER
Gleneagles Medical Centre
6 Napier Road #06-16, Singapore 258499
NOVENA
Mount Elizabeth Novena
38 Irrawaddy Road, #10-48/49, Singapore 329563
JOO CHIAT / EAST COAST
Parkway East Hospital
#05-08, 319 Joo Chiat Place, Singapore 427989
THOMSON
Mount Alvernia Hospital
#08-62, Medical Centre D, 820 Thomson Road, Singapore 574623
FARRER PARK
Farrer Park Medical Centre
#14-12, 1 Farrer Park Station Road, Singapore 217562
What the platform changes
What the platform changes
100+
Da Vinci Xi rectal cancer cases
The learning curve for robotic rectal surgery is steep. Having now performed more than 100 Da Vinci Xi rectal cancer cases, Dr Sulaiman has seen the platform’s advantages most clearly in low rectal tumours, narrow male pelvises, and cases where nerve preservation is the priority alongside oncological clearance.
Source: Dr Sulaiman Bin Yusof, clinical practice
Low rectal tumours
Where the dissection runs deepest
A narrow male pelvis
Least room for rigid instruments
Nerve preservation first
Function alongside oncological clearance
Robotic surgery is not required for every rectal cancer patient, and the approach is chosen from your own tumour, stage and anatomy. How rectal and colon cancer differ explains why the tumour’s location drives that choice.
About 17%
Laparoscopic conversion to open surgery
When laparoscopic rectal surgery cannot be completed minimally invasively, conversion to open surgery is required. Published data shows that conversion carries significantly higher complication and mortality rates, which is why reducing the risk of it matters for patient safety.
Source: COLOR II randomised trial
Laparoscopic rectal cancer surgery, by whether it stayed keyhole
- Converted to open
- About 17%
- Completed keyhole
- About 83%
Source: COLOR II randomised trial
His own account
Why he moved this operation onto the robot.
Dr Sulaiman on what changed when he stopped operating on rectal cancer laparoscopically and started operating on the Da Vinci Xi.
When I first started performing laparoscopic rectal cancer surgery, I would spend days planning and mentally rehearsing every step of the operation. Rectal surgery deep within the pelvis is technically demanding, and outcomes depend heavily on the coordination of the entire operating team.
In laparoscopic surgery, the quality of the operation is influenced not only by the surgeon’s skill, but also by the experience of the camera assistant and the surgical assistant. Stable exposure and precise visualisation during deep pelvic dissection can make a significant difference in how cleanly the operation proceeds.
Transitioning to robotic surgery on the Da Vinci Xi changed many aspects of that experience. The platform gave me direct, stable control over the camera, the exposure and the instrument movement throughout the operation, independent of an assistant. In difficult low pelvic cases especially, the improved precision was immediately apparent.
The learning curve for robotic rectal surgery is steep, and mastering it takes sustained volume rather than occasional use. Having now performed more than 100 Da Vinci Xi rectal cancer cases, I have seen the platform’s advantages most clearly in low rectal tumours, narrow male pelvises, and cases where nerve preservation is the priority alongside oncological clearance.
Precision in the pelvis
Superior 3D visualisation and instrument dexterity in the narrow, deep anatomical space where rectal tumours sit.
Lower conversion rates
A lower risk of converting to open surgery than laparoscopic, in pooled published analyses, and a conversion is itself a step that increases complication risk.
Nerve preservation
Enhanced ability to identify and protect the autonomic nerves controlling bladder and sexual function during pelvic dissection.
Faster recovery
Smaller incisions, less tissue trauma, and reduced blood loss compared with open surgery translate to shorter hospital stays.
Robotic surgery is not required for every rectal cancer patient. Treatment is always individualised based on tumour location, stage, anatomy, and overall condition. Where the segment that has to come out lies further up the bowel rather than in the rectum, the operation is a laparoscopic hemicolectomy or a robotic colectomy or anterior resection instead.
What it is
Removing the rectum with its envelope, from a console.
Robotic rectal cancer surgery is an advanced minimally invasive approach to removing rectal tumours with precision deep within the pelvis.
The standard oncological operation is called a total mesorectal excision, or TME: the complete removal of the rectum together with its surrounding mesorectal envelope, which contains the lymph nodes and the tissue through which cancer spreads.
The Da Vinci Xi system enables TME to be performed robotically throughout all stages of the operation, without the need to reposition the robot between the abdominal and the pelvic phases. The surgeon operates from a console, controlling robotic arms that translate finger movements into micro-movements inside the body, with tremor filtration, 3D high-definition vision, and instrument wrist rotation that is not achievable with standard laparoscopic tools.
Laparoscopic and robotic, side by side
Both are keyhole operations. What separates them is what the surgeon can see, what the instruments can do at the bottom of the pelvis, and who is holding the camera.
| Feature | Laparoscopic | Robotic, Da Vinci Xi |
|---|---|---|
| Vision | 2D | 3D HD with depth |
| Instruments | Rigid, straight | Wristed, 7 degrees of freedom |
| Pelvic access | Limited | Optimised |
| Camera control | Assistant-held | Surgeon-controlled |
| Conversion to open | About 17% | Lower in pooled analyses |
| Ergonomics | Counter-intuitive | Intuitive, natural |
The laparoscopic conversion figure is from the COLOR II randomised trial. The robotic comparison comes from a 2024 meta-analysis of robotic against laparoscopic rectal cancer surgery covering 25,458 patients, which found lower conversion rates. The ROLARR randomised trial, Jayne et al., JAMA, 2017, 471 patients across 29 sites, found no significant difference, so treat the direction as supported by pooled data rather than settled by a single trial.
How rectal cancer is diagnosed and staged before any operation is planned is set out on the colorectal cancer page. The keyhole version of the sphincter-preserving operation is on the laparoscopic anterior resection page.
Why it is demanding
Rectal cancer surgery is technically demanding, and here is why.
The rectum sits deep within the pelvis, a narrow, bone-encased cavity surrounded by structures that must be preserved throughout the operation.
Every difficulty in this operation follows from one fact: the rectum sits at the bottom of a narrow, bone-encased pelvis.
The narrow space problem
Operating at the bottom of the pelvis with laparoscopic instruments is like working in a deep, narrow funnel with rigid tools. Even experienced laparoscopic surgeons face technical limitations in achieving consistent TME quality in low pelvic cases.
Nerve preservation
The autonomic nerve plexuses governing bladder function, urinary continence, and sexual function run directly alongside the surgical dissection plane. These nerves are paper-thin and difficult to visualise at the relevant depth with a 2D camera.
Sphincter preservation
For tumours in the middle and lower rectum, the goal is to achieve oncological clearance while preserving the anal sphincter and avoiding a permanent stoma. The closer a tumour sits to the sphincter, the more precise the distal dissection must be.
The consequence of conversion
When laparoscopic rectal surgery cannot be completed minimally invasively, conversion to open surgery is required. Published data shows conversion carries significantly higher complication and mortality rates. Reducing conversion risk matters for patient safety.
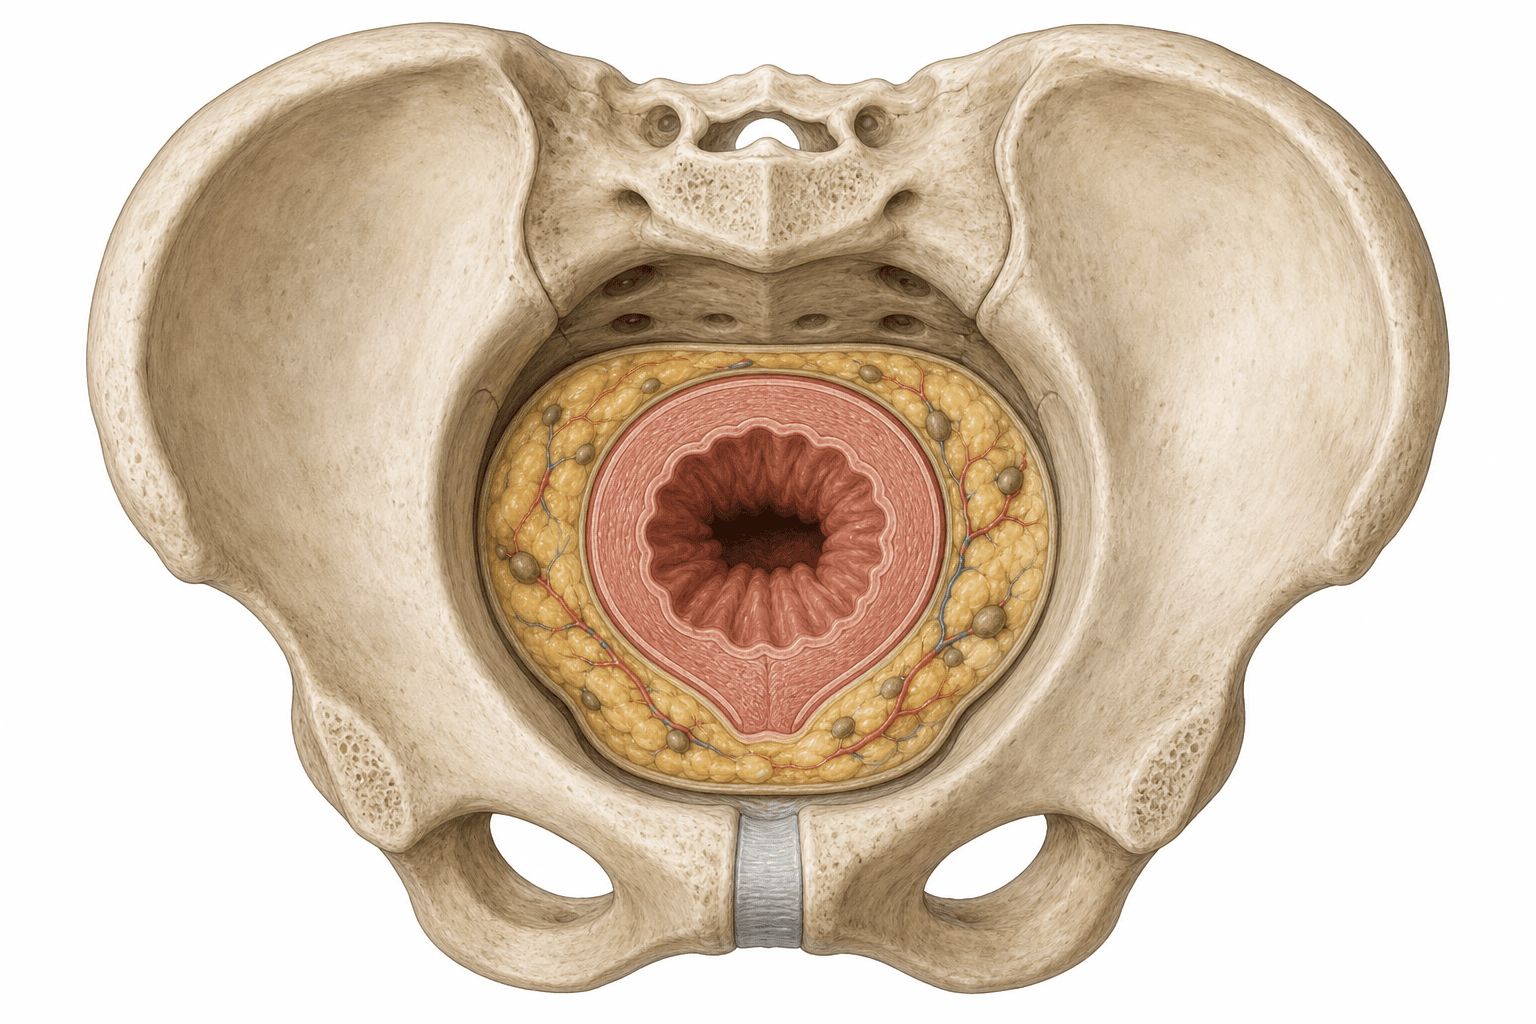
The yellow envelope around the rectum is the mesorectum, and the lymph nodes inside it are the reason it is removed whole rather than cut through. It has to come out through the bony ring drawn around it. Illustration, not a photograph, and not yet certified by Dr Sulaiman.
The case for robotic TME
The quality of the excision is what decides the long-term outcome.
TME quality is the most important determinant of long-term rectal cancer outcomes. An incomplete or disrupted mesorectal excision increases the risk of local recurrence regardless of surgical approach.
Robotic surgery’s advantage is in the consistency with which a high-quality TME can be achieved in technically difficult cases.
- 3D visualisation clarifies the correct dissection plane even at the pelvic floor, where laparoscopic views are limited
- Wristed instruments allow precise dissection in the narrow space without the leverage problems of straight laparoscopic tools
- Stable camera control eliminates the variability introduced by assistant-dependent laparoscopic camera holding
- Tremor filtration is particularly relevant during the most delicate phases of nerve-sparing dissection
25,458
Patients in the pooled comparison
Published meta-analysis comparing robotic against laparoscopic rectal cancer surgery across more than 25,000 patients found robotic surgery to be associated with significantly lower conversion rates and comparable oncological outcomes, including lymph node harvest and margin clearance.
Source: Meta-analysis of robotic against laparoscopic rectal cancer surgery, 2024
That finding comes from pooled data rather than from a single trial, and the largest randomised trial on the question disagrees with it. ROLARR, Jayne et al., JAMA, 2017, randomised 471 patients across 29 sites and found no significant reduction in conversion to open surgery with the robotic approach. Both results are stated here because both are true of what they measured, and because the honest version of this argument is that robotic assistance is well suited to difficult pelvic cases rather than proven superior in every one.

A training board rather than a patient, but the instruments and the movement are the real ones. Dr Sulaiman filmed this in his own theatre.
Who benefits most
Five situations where robotic assistance changes the operation most.
Not every rectal cancer patient requires robotic surgery. Dr Sulaiman’s assessment takes into account tumour location, pelvic anatomy, body habitus, and functional preservation priorities. Robotic assistance is most clearly advantageous in the following situations.
Low rectal cancer
Tumours within 5 to 10 cm of the anal verge, where the dissection is deepest and the nerve structures most at risk.
Men with a narrow pelvis
The male pelvis is anatomically narrower, which makes the technical constraints of laparoscopic instruments more pronounced.
Obesity
Increased pelvic fat makes visualisation and dissection more difficult, and the camera stability of the Da Vinci Xi is more consequential in challenging conditions.
Sphincter preservation cases
Where the tumour is close to the anal sphincter and the goal is clearance without a permanent stoma.
Nerve-sparing priority
Patients for whom preserving bladder and sexual function is a stated priority alongside oncological clearance.
Which approach suits your case is decided from your imaging and your anatomy, before anything is scheduled.
Quality of life
Clearing the cancer, and keeping the function, are both goals.
Effective rectal cancer surgery balances two goals: complete oncological clearance and preservation of function. With precise technique, both are achievable in selected patients.
Bladder function
The pelvic autonomic nerves controlling urinary continence and bladder emptying run close to the dissection plane. Careful nerve-sparing TME reduces the risk of post-operative urinary retention, one of the most common functional complications of rectal cancer surgery.
Sexual function
In men, the nerves governing erectile function lie alongside the lateral dissection planes. In women, the equivalent structures affect vaginal sensation and lubrication. Robotic 3D visualisation improves the ability to identify and preserve these structures where it is oncologically safe to do so.
Bowel function
Changes in bowel habit are common after rectal cancer surgery and are related primarily to the length of bowel removed and the level of the anastomosis rather than to the surgical platform. Patients should expect some adjustment in bowel frequency, particularly in the first year.
Stoma
A temporary diverting stoma is frequently created at the time of surgery to protect the anastomosis while it heals. This is usually reversed in a second procedure after approximately three months. A permanent stoma is required when the tumour is so close to the sphincter that preservation is not oncologically safe.
3 months
Before a temporary stoma is usually reversed
A temporary diverting stoma is frequently created at the time of surgery and is usually reversed after approximately three months. It is not the same thing as a permanent stoma, which is needed only when the tumour sits so close to the sphincter that preserving it would not be oncologically safe.
Source: Dr Sulaiman Bin Yusof, clinical practice
Created at surgery
To protect the new join while it heals
The join heals
Roughly three months
Reversed
In a second, smaller procedure
What to ask a surgeon
Five questions worth asking before you choose anyone.
Experience with robotic surgery varies considerably between surgeons. When choosing a specialist for robotic rectal cancer surgery in Singapore, patients should feel empowered to ask the following.
How many robotic rectal cancer cases have you performed?
What is your personal conversion rate to open surgery?
What is your approach to nerve preservation in low rectal cases?
What proportion of your rectal cancer patients require a permanent stoma?
How do you assess whether robotic surgery is appropriate for my specific anatomy and tumour?
These are reasonable questions to put to any surgeon, this one included, and Dr Sulaiman will answer all five at consultation.
When to seek an opinion
When a specialist opinion is worth having.
Most people arrive at this page after a test result rather than after a symptom. What the test itself involves, and what the day looks like, is on the colonoscopy page.
A new diagnosis of rectal cancer, or a suspicious rectal polyp found at colonoscopy, should be assessed rather than watched.
- A new diagnosis of rectal cancer, or a suspicious rectal polyp found at colonoscopy
- Tumours located in the middle or lower rectum, where surgical complexity is highest
- Questions about sphincter preservation and stoma avoidance
- Seeking a second opinion on minimally invasive or robotic surgery options
- Concerns about bladder or sexual function preservation during surgery
You do not need a referral to see Dr Sulaiman. Same-day and same-week appointments are available across five clinic locations in Singapore.
Evidence on this page
Clinical information on this page reflects Dr Sulaiman’s practice and is informed by published evidence including a meta-analysis of robotic against laparoscopic rectal cancer surgery covering 25,458 patients, 2024; a Da Vinci Xi first 100 rectal cancer cases series, Istanbul Medical Journal, 2019; COLOR II randomised trial data on laparoscopic rectal cancer conversion rates; and the ROLARR randomised trial, Jayne et al., JAMA, 2017. This page is for informational purposes only and does not constitute medical advice.
Cost and cover
What the operation can cost, and how it is usually covered.
Many rectal cancers are removed with an anterior resection, and for that operation done as minimally invasive surgery, MOH's transacted bill data puts the median private-hospital inpatient bill at $58,411 (source: Ministry of Health, Singapore, fee benchmarks and bill information for SF701C, opens in a new tab) including GST, with the middle half of bills between $50,423 and $68,084 (source: Ministry of Health, Singapore, fee benchmarks and bill information for SF701C, opens in a new tab), before Medisave and insurance payouts.
Robotic surgery is one form of minimally invasive surgery, so the benchmark is the closest published reference rather than a robotic quote, and fees at the higher end tend to involve recurrent surgery, adhesions or more complex cases such as larger tumours invading surrounding structures. The operation is Medisave-claimable, Integrated Shield Plans and corporate insurance are accepted at the clinics, and the clinic team will walk you through the estimate for your own operation at the specialist consultation.
Common questions
The questions that come up before robotic rectal surgery.
How does robotic surgery compare with laparoscopic surgery for rectal cancer?
Both are safe minimally invasive approaches. For complex rectal cases, particularly low tumours and narrow male pelvises, robotic surgery is associated with lower conversion rates to open surgery, which reduces associated complication risk. Oncological outcomes including lymph node harvest and margin clearance are comparable between the two approaches in published data. The conversion finding comes from pooled analyses rather than from a single trial: the ROLARR randomised trial, Jayne et al., JAMA, 2017, 471 patients across 29 sites, found no significant difference in conversion between the two.
Do I actually need robotic surgery for my rectal cancer?
The technical advantages of robotic surgery are most relevant for low rectal tumours, male patients with narrow pelvises, obese patients, and cases where nerve preservation is a priority. For straightforward high rectal or sigmoid cancers, laparoscopic surgery often achieves equally good results. Dr Sulaiman will assess your specific anatomy and tumour on imaging before recommending an approach.
Will I need a stoma?
Whether a temporary or permanent stoma is required depends on the tumour's location relative to the sphincter, the quality of the anastomosis, and the patient's overall fitness. Robotic surgery improves the precision of low anastomoses, which may assist sphincter preservation in selected cases. A temporary diverting stoma is commonly created to protect the join while it heals and is typically reversed after three months.
Is the recovery really faster than with open surgery?
Compared with open surgery, yes. Robotic and laparoscopic surgery both offer significantly faster recovery, less post-operative pain, and shorter hospital stays. The difference in recovery between robotic and laparoscopic surgery is more modest, though robotic surgery is associated with lower blood loss and conversion rates in complex cases.
Is robotic rectal cancer surgery claimable under MediSave or insurance?
Yes. Robotic rectal cancer surgery is generally covered by Integrated Shield Plans and is MediSave-claimable (source: CPF Board, using MediSave for hospitalisation, opens in a new tab), subject to plan limits and applicable surgical procedure codes. Please contact our clinic team for guidance on pre-authorisation.
What is total mesorectal excision, or TME?
TME is the gold-standard surgical technique for rectal cancer, involving complete removal of the rectum together with its surrounding mesorectal envelope, the tissue containing the lymph nodes and fatty tissue through which cancer spreads. Quality of TME is the single most important determinant of local recurrence risk.
Book a consultation
Considering robotic surgery? Start with an assessment of your own anatomy.
Book a consultation with Dr Sulaiman for an assessment of your own tumour, your pelvic anatomy and the approach that fits them. You do not need a referral, and same-day and same-week appointments are available across five clinic locations in Singapore.